Would you let them treat your mother?
The criteria for a good fit is specific to your clinic, your team, and your community. Here's how to define it.


Most executives can describe physician fit in one direction only—what it looks like when they’ve hired a physician that doesn’t work out.
"Not a culture fit." "Toxic." "Makes the staff turn the other way."
The C-suite hears this feedback from clinic managers on a loop. When the next search starts, that list of complaints becomes the definition. The hire must “not be like the last one.”
Is that a definition of a bad fit, or is it simply a reaction to one?
It is easier to say what you don’t want, and harder to say what you do. Most executives, when asked what kind of physician they are looking for, are relieved to get an idea of it on paper. This takes work.
Defining fit requires looking past the complaints at the specific behaviors the last bad placement didn't have, and looking at the ones your best physician already does.
These are the steps I walk hospitals through before their next physician search begins.
What "Bad Fit" Actually Means at the Clinic Level
Knowing exactly what you don't want is a reasonable starting point. It’s important to remember that "not a culture fit" and "toxic" are both conclusions, not criteria that get you closer to a better fit down the line.
The real work is getting underneath what those words mean.
Does the physician say hello in the hallway, or look the other way? When a nurse pushes back, how do they respond? Do they carry frustration into the room, or leave it at the door?
These are things the clinical team already knows. Talk through these scenarios with them and they become screening criteria.
60% of a hospital's operating cost* goes to staffing for patient care.
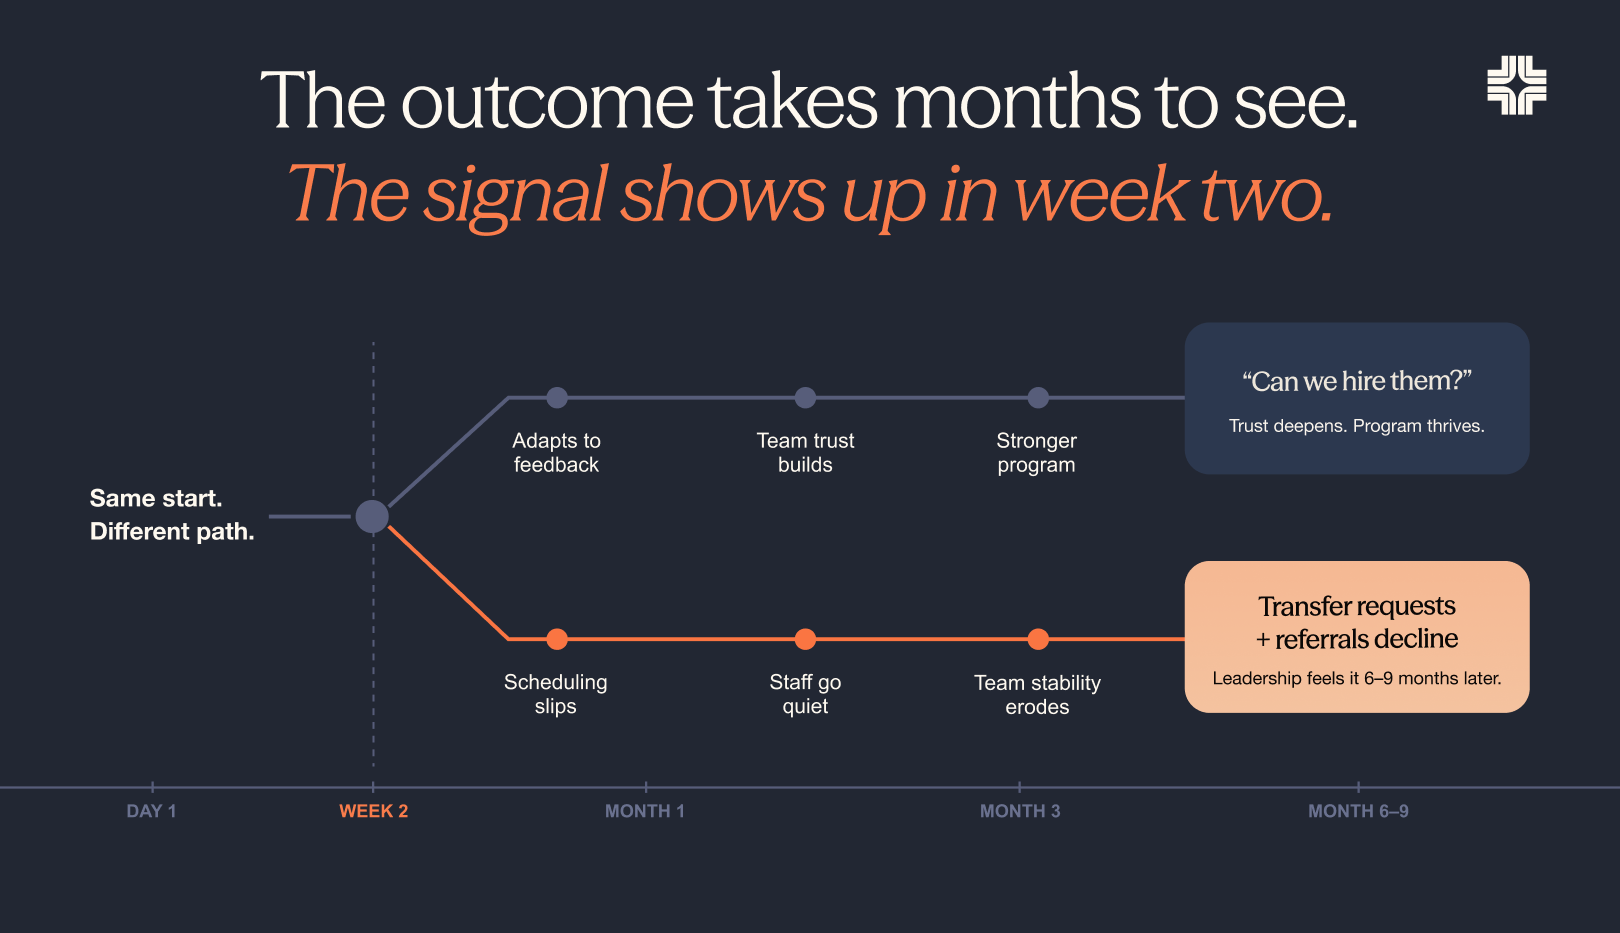
Defining fit at the clinic level has a direct impact on staff retention.
Staff retention has a direct impact on cost.
In a previous edition of Preferred Pulse, we covered how to get independent contractor costs down to a W-2 equivalent.
*source: American Hospital Association
The discovery process I run starts with writing down the negatives and then putting them aside.
The Question Worth Asking
Would you let this physician treat your mother?
It's a question I hear from other physicians, colleagues, and executives more than any other. It cuts past credentials straight to trust.
Hospitals already have core values. Most only use them when something goes wrong.
Use them on the front end. Rate candidates on whether they exhibit those values day to day. Use a thumbs up or thumbs down scoring system across five criteria you’ve defined.
When you define fit before the search starts, there’s less friction at onboarding and the physician stays longer. The staff notice the difference.
Our discovery process starts here. The goal is to build a specific description of someone who fits your program, your team, and your community, and then go find that person. I’ve written about how we measure physician fit here.
Let’s get to work.